
rQ JOURNAL
A slow MTHFR result is not a reason to take more folic acid. It is a reason to stop using it.
Folic acid should be avoided entirely if you have a slow MTHFR variant. It is not a gentler form of folate. It blocks the folate receptor, the doorway cells use to take folate in, and it can make the problem worse.
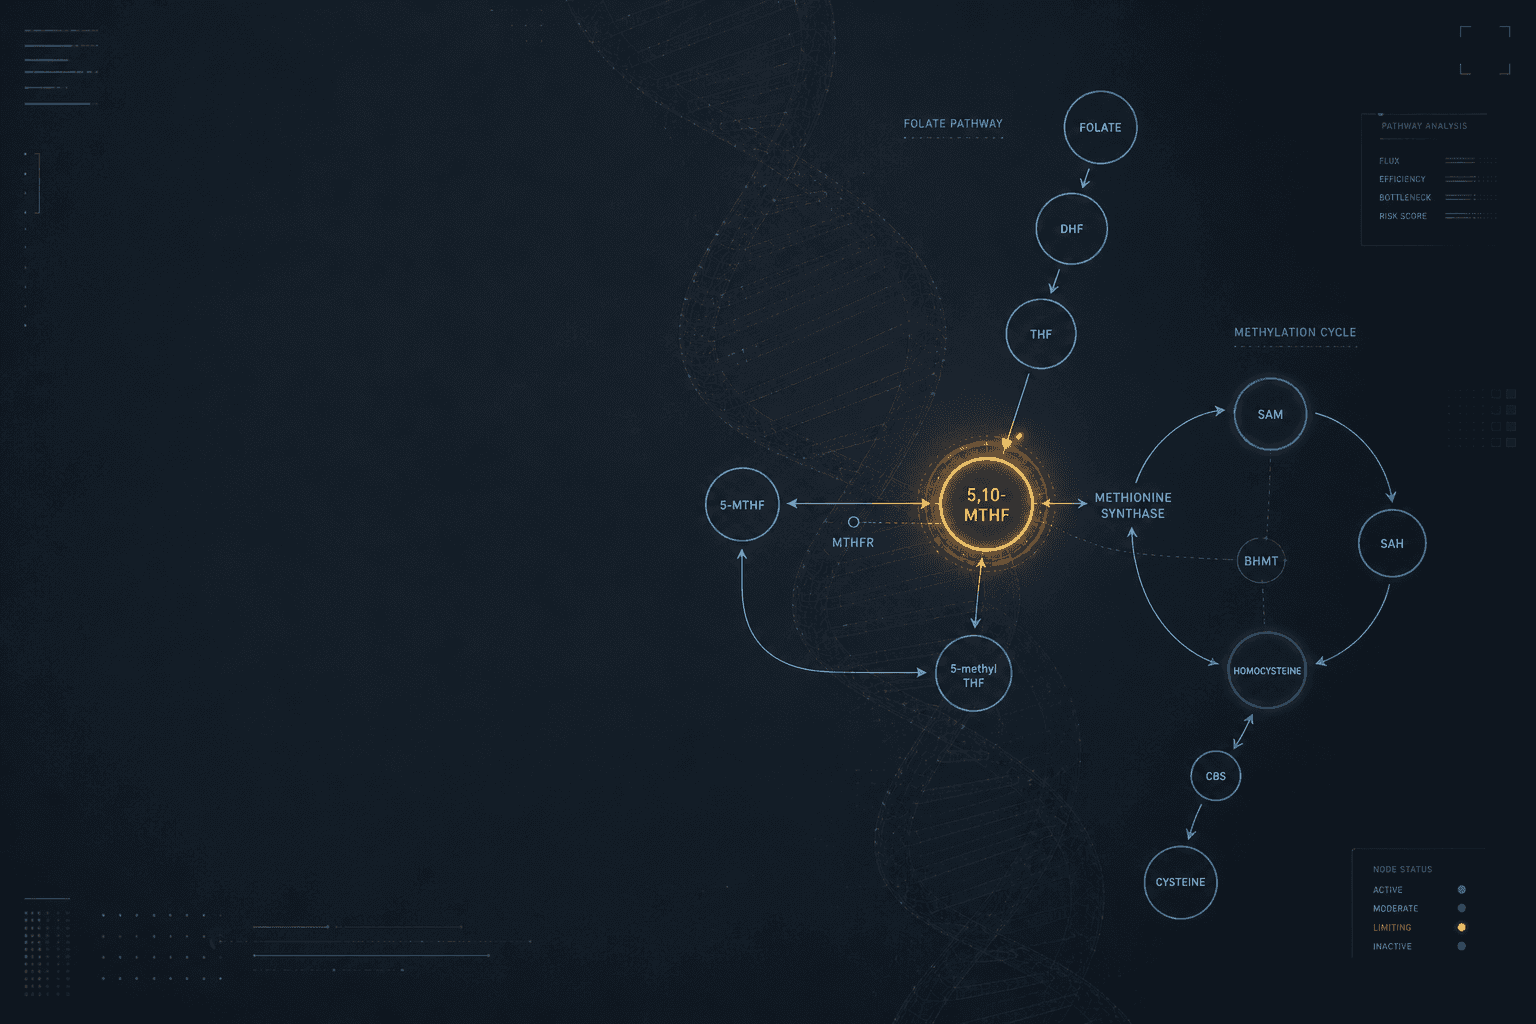
MTHFR is the enzyme that helps finish folate into methylfolate, the form your body actually uses. When that enzyme runs slowly, the pathway already has less reserve. Folic acid, the synthetic form in many supplements and fortified foods, does not slip through that narrow step and help. It parks on the receptor. Usable folate cannot get in as easily. The slow enzyme is left with less of the right material, not more.
So the useful question is not, "How do I fix my MTHFR?" It is: Where is folic acid still getting in, and what happens if it is removed completely?
Avoid folic acid entirely
Do not treat folic acid as optional, "fine in food," or close enough to folate. For a slow MTHFR variant, folic acid should be avoided entirely.
That means supplements, prenatals, B complexes, energy drinks, and fortified grains that list folic acid. If the label says folic acid, it is the form to remove. "Folate" on a supplement panel is not always the same thing. Read the line. Folic acid, methylfolate, and folinic acid are different molecules.
Avoiding it entirely matters because partial avoidance still leaves the receptor occupied. A morning prenatal with folic acid can block the rest of the day's food folate and any methylfolate you add later. The receptor does not prefer the better form if folic acid is already sitting on it.
How the block works
Folate receptors move folate into cells, including into the brain. Folic acid binds those receptors more tightly than methylfolate, then does not transport through them the way the active form does. The dock is taken. The cargo the cell can use is left outside.
Folic acid also has to be converted before MTHFR can do anything with it. That early conversion depends on an enzyme called DHFR, which is slow in humans and saturates easily. What does not convert stays in the blood as unmetabolized folic acid. That leftover molecule is the one competing for the receptor.
A slow MTHFR variant sits later in the same pathway. It already makes methylfolate with less reserve, especially under low folate status, high demand, inflammation, alcohol, certain medications, or poor absorption. Block the receptor in front of that slow step, and you do not support the gene. You add a second constraint. Matters get worse: less usable folate inside the cell, a harder time recycling homocysteine, and a methylation system running on empty while the label says you are "on folate."
What "slow MTHFR" actually means
MTHFR stands for methylenetetrahydrofolate reductase. It helps produce 5-methyltetrahydrofolate, the main circulating folate. That form works with vitamin B12 to recycle homocysteine into methionine and to feed SAMe, the body's main methyl donor.
The variants people hear about most are C677T and A1298C. Two copies of C677T slow the enzyme the most. Slow does not mean broken, and it is not a life sentence. It means the finishing step has less slack. Folic acid spends that slack instead of protecting it.
How this shows up
People with a slow variant often recognize a cluster. Fatigue and poor recovery. Brain fog or a shorter fuse when demand rises. Histamine or chemical sensitivity sitting next to other methylation strain. A history of feeling worse on B vitamins or "folic acid made me feel off." Pregnancy planning that started with a folic acid prenatal and then symptoms shifted.
Labs can miss this. Many folate tests do not separate unmetabolized folic acid from real folate, so a result can look normal while cells are underfed. Homocysteine may stay high even after years of "folate." None of that proves the gene is the only cause. It is a reason to remove folic acid completely and see the pathway more clearly, with a clinician if you are pregnant, deficient, or on prescribed folate.
Some people also feel wired or irritable if methylfolate is pushed too hard, too fast, especially when B12 is low. That reaction is a dose and cofactor problem. It is not a reason to go back to folic acid. Folic acid is the form to avoid, not the safer backup.
What to use instead, and what still matters
The aim is usable folate reaching the receptor, not a bigger dose of the blocking form. Food folate and active forms such as methylfolate or, in some cases, folinic acid do not require the same early conversion and do not occupy the receptor the way folic acid does. Form still has to be matched to the person. Dose still matters. B12 still has to be present. Gut absorption, sleep, alcohol, and inflammatory load still change demand.
A capsule cannot outrun a day of fortified folic acid. Avoiding folic acid entirely is the first move. Choosing a usable form comes after the block is gone, not instead of removing it.
Start asking better questions
Instead of "Which folate should I add?" start with:
Where is folic acid still entering: supplements, prenatals, drinks, or fortified food?
Have I removed it entirely, or only cut the obvious bottle?
Is my folate lab measuring usable folate, or a mix that includes unmetabolized folic acid?
What happened after folic acid was stopped, before any new methylated vitamin was added?
Is B12 adequate, or am I adding methylfolate onto an empty partner step?
What else is stressing methylation at the same time?
When to get medical evaluation
This is pattern education, not a personal prescription. If a clinician has you on a prescribed folic acid product, especially in pregnancy or for a documented deficiency, do not stop it in secret. Bring this mechanism to that visit and ask about avoiding folic acid entirely and using a form that does not block the folate receptor. Significantly high homocysteine, clotting history, recurrent pregnancy loss, or new neurologic symptoms need medical evaluation. Common MTHFR variants are not the same as rare severe enzyme deficiency. Do not self-prescribe high-dose methylated vitamins from a gene screenshot.
The rQ perspective
A slow MTHFR variant is a narrower finishing step. Folic acid makes that narrower step worse by blocking the folate receptor and leaving unmetabolized folic acid in the way. The clear move is to avoid folic acid entirely, then ask whether the cells are finally getting a form they can use.
If you want a clearer read on how folate handling sits beside other predispositions, pathways, and drivers, start with the free assessment at www.rq.one. It will not diagnose you. It will help organize the questions your labs and symptoms have been answering incompletely.
Chase answers, not symptoms.
Take the rQ assessment
Back to Journal